International experts establish first consensus guidelines for diagnosing hypochondroplasia
The recommendations cover growth patterns, x-rays, FGFR3 testing, family history and prenatal findings.
Diagnosing hypochondroplasia can be challenging. The signs can be subtle, especially in young children, and the condition can look different from one person to another. Now, an international group of clinicians, researchers and patient representatives has developed the first consensus recommendations to make diagnosis clearer and more consistent.
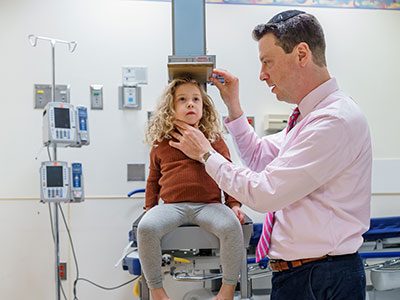
Published in Nature Reviews Endocrinology, the recommendations bring together clinical features, growth patterns, imaging and genetic testing in one framework. Andrew Dauber, MD, chief of Endocrinology and director of the Center for Precision Medicine and Genomics Research at Children’s National, led the work.
The big picture
Hypochondroplasia is a rare genetic skeletal condition associated with disease-causing variants in the FGFR3 gene. It often causes disproportionate short stature and relative microcephaly, or a head size that is larger in proportion to the body.
But there’s no single way that the condition looks. Signs may be difficult to spot in infancy, and children with milder or atypical features can be especially challenging to diagnose. Getting the diagnosis right matters. Without clear answers, families may face delays in getting the monitoring and care their child needs.
The hold-up in the field
Until now, clinicians around the world haven’t had a shared set of criteria for diagnosing hypochondroplasia. To address the gap, international experts and patient representatives reviewed the available evidence and drew on their collective experience. Using a two-stage Delphi process, they reached consensus on a standardized approach to diagnosis.
The new framework includes major and minor diagnostic criteria and categories for definitive, suspected and genetically unconfirmed hypochondroplasia. Clinicians start with a patient’s physical and clinical features, using genetic testing to confirm or clarify the diagnosis when available.
Moving the field forward
The recommendations cover growth patterns, x-rays, FGFR3 testing, family history and prenatal findings. They also offer guidance on when brain magnetic resonance imaging (MRI) may be helpful, including for children with seizures, developmental concerns or increasing head circumference.
“There have been different practices around the world for evaluating children for this diagnosis, and it was gratifying to have all of us agree on a unified approach,” Dr. Dauber said. “These recommendations give clinicians a clear reference for evaluating patients and reaching a definitive diagnosis.”
The framework is designed to work across healthcare settings, including where genetic testing isn’t readily available.
The patient benefit
For families, a more consistent approach could mean getting answers sooner and reducing uncertainty. An earlier diagnosis can also help connect children with appropriate monitoring, developmental services, genetic counseling and other care.
That consistency is becoming more important as potential growth-modifying treatments advance through clinical trials. The new guidelines do not determine who is eligible for treatment, but they can help clinicians and researchers identify patients using the same standards.
Children’s National is a leading center for hypochondroplasia care and research and serves as the lead site for several clinical trials. Next, the team plans to evaluate how well the recommendations work in everyday clinical practice and refine them as new evidence emerges.
Read the full guidelines, Diagnosis of hypochondroplasia: International Delphi consensus recommendations, in Nature Reviews Endocrinology.